
Retatrutide pens in the UK: what the research can and cannot tell us
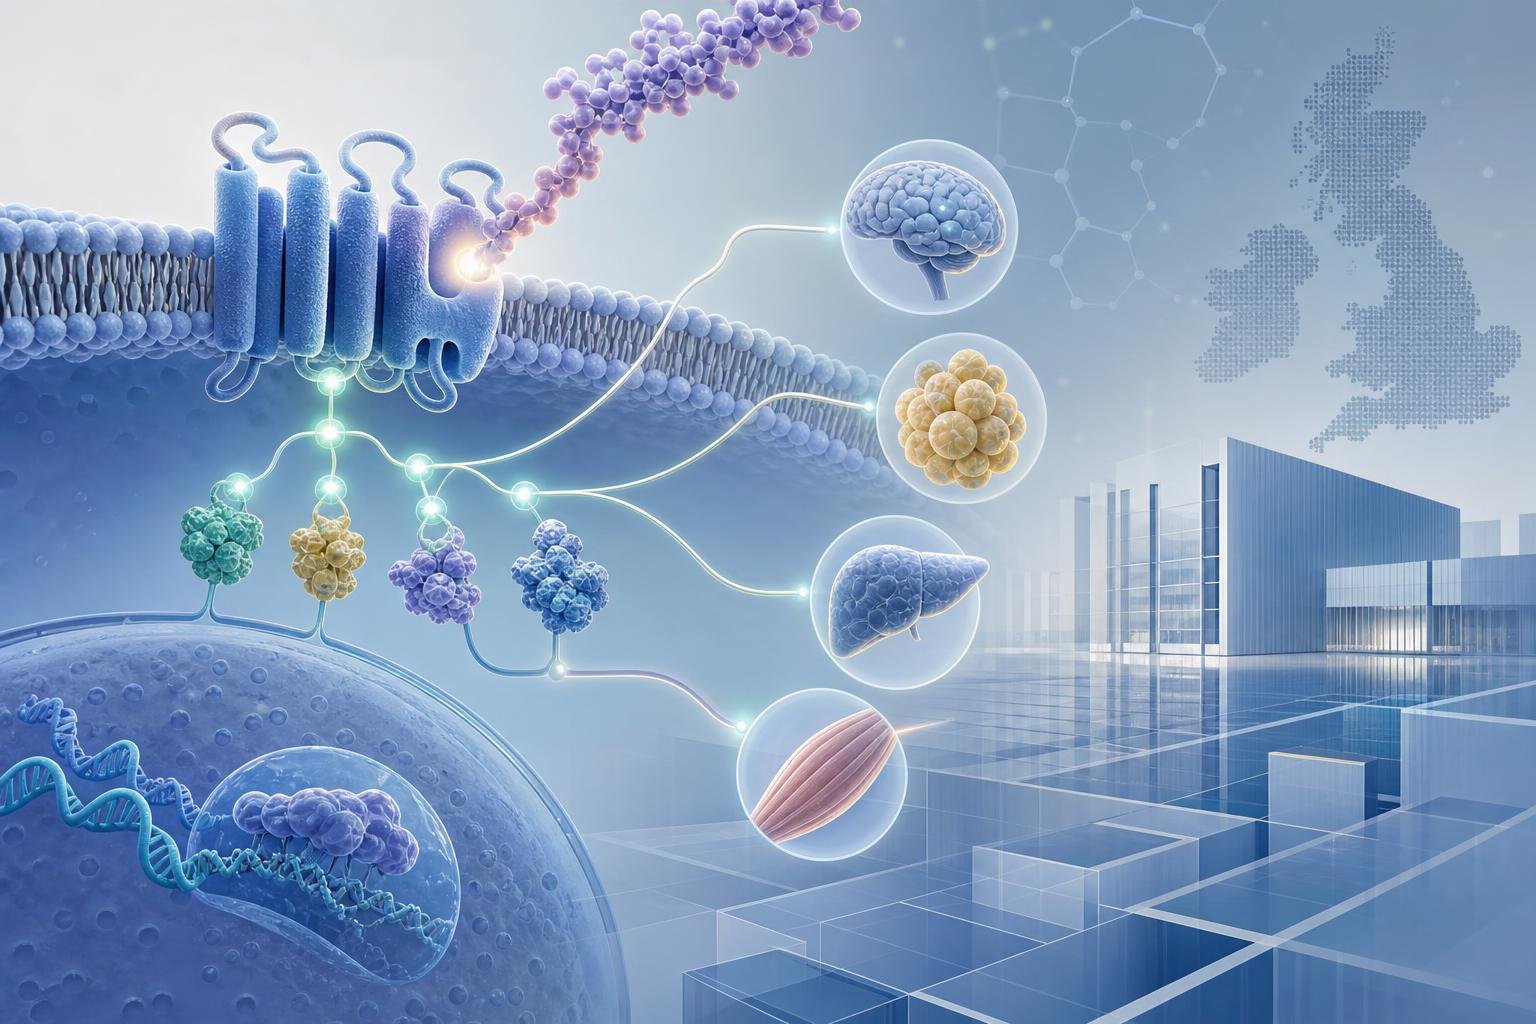
Short answer: Retatrutide is an investigational incretin-based medicine, and searches for “retatrutide pens UK” should be understood as interest in the research and potential delivery format, not evidence of a licensed UK product. The available public evidence should be read cautiously: it can explain the science, but it cannot support personal use, sourcing or treatment decisions.
What is retatrutide?
Retatrutide is a research-stage medicine designed to act on three hormone receptors involved in appetite, blood sugar regulation and energy balance. It belongs to the wider scientific field of incretin-based therapies, a group of medicines that imitate or influence gut hormones released after eating.
The three receptor targets commonly discussed in relation to retatrutide are:
- GLP-1 receptor: linked with appetite signalling, insulin release when glucose is present, and slower stomach emptying.
- GIP receptor: involved in insulin secretion and metabolic signalling after food intake.
- Glucagon receptor: involved in liver glucose regulation and energy metabolism.
Because retatrutide is designed to interact with all three, it is often described in research contexts as a “triple agonist” or “tri-agonist”. That label refers to receptor activity, not to a guaranteed clinical outcome for any individual.
Why are people searching for retatrutide pens in the UK?
The word “pens” appears in searches because several established injectable metabolic medicines are supplied in pre-filled pen devices. A pen is simply a delivery device: it does not determine whether a medicine is licensed, safe, effective, appropriate or available.
For retatrutide, the important distinction is between clinical research and regulated medical supply. A medicine can be studied in trials long before any final decision is made about whether it should be authorised, what it should be called, which patients it may be used for, and what device or packaging might be used. Public interest in a possible pen format should therefore not be confused with confirmation of a UK product.
Research status versus real-world use
Clinical development normally moves through stages. Early studies explore safety, tolerability and biological activity. Later studies are larger and are designed to answer more specific questions about benefits and risks in defined groups of participants. Regulators then review evidence before a medicine can be marketed for a particular use.
In the UK, medicines are regulated through formal authorisation processes. That matters because injectable medicines require quality-controlled manufacturing, clear labelling, device testing where relevant, cold-chain or storage evidence when needed, and pharmacovigilance systems to monitor safety after approval. None of these can be assumed from search interest or from informal online discussion.
As a practical editorial point, it is safest to treat retatrutide as a research topic unless a recognised regulator and official prescribing information state otherwise. This article does not provide instructions on obtaining, preparing or using retatrutide.
How retatrutide relates to other incretin medicines
Retatrutide is part of a broader research trend: using gut-hormone pathways to influence metabolic processes. Some medicines in this general area act mainly on GLP-1 receptors. Others act on both GLP-1 and GIP receptors. Retatrutide is being studied because it adds glucagon receptor activity to that pattern.
These relationships are scientifically interesting, but they do not make the medicines interchangeable. Differences in receptor activity, molecule structure, dose design, side-effect profile, trial population and regulatory approval can all change how a medicine is assessed. It is therefore misleading to infer that information about one incretin medicine automatically applies to another.
What can research tell us?
Good clinical research can help answer several questions:
- whether a medicine has measurable effects in a defined trial population;
- what adverse effects are observed under monitored conditions;
- how outcomes compare with placebo or another comparator, if included;
- which groups were studied and which were not;
- what uncertainties remain after the trial.
For a developing medicine, uncertainty is not a flaw in the conversation; it is the point of doing trials. Early excitement can be replaced by a more balanced view as larger and longer studies report results. Safety signals may also become clearer only when more people have been studied over more time.
What research cannot tell an individual reader
Even well-designed studies cannot tell an individual member of the public whether an investigational medicine is suitable for them. Trial results apply to groups under carefully controlled criteria. A person’s medical history, other medicines, pregnancy status, gastrointestinal conditions, endocrine disorders and cardiovascular risk can all affect clinical decision-making.
There are also product-quality issues. With any medicine discussed online before or around the time of formal approval, readers may encounter unreliable claims, unofficial supply routes or materials that are not what they claim to be. An injectable product is not just an active ingredient; sterility, concentration, formulation, storage, device accuracy and traceability all matter.
Safety considerations in plain language
Incretin-based medicines can affect the digestive system and metabolic signalling. Commonly discussed class effects for related medicines include nausea, vomiting, diarrhoea, constipation and reduced appetite. More serious risks and contraindications depend on the specific medicine and must be evaluated through its own evidence base.
Because retatrutide targets multiple receptors, it should not be assumed to have the same safety profile as any single- or dual-receptor medicine. The only responsible approach is to wait for robust trial data, regulatory review and official product information, rather than relying on analogies or social media claims.
How to read future retatrutide news
When new information appears, check what kind of evidence it is. A conference abstract, company announcement, peer-reviewed article and regulatory document are not the same thing. Useful questions include:
- Was the study randomised and controlled?
- How many participants were included?
- How long were they followed?
- What outcomes were measured?
- Were adverse events clearly reported?
- Was the population similar to the group being discussed?
This approach keeps the focus on evidence rather than hype. It is especially important for a topic where public interest may run ahead of settled clinical practice.
FAQ
Is retatrutide the same as a pen?
No. Retatrutide refers to the investigational medicine. A pen, if used for any injectable medicine, is only a delivery device. The device format does not establish regulatory approval or clinical suitability.
Does “UK” in the search mean it is available in Britain?
No. Search demand only shows that people are looking for information. It does not prove UK authorisation, NHS use, private availability or product supply.
Can research articles guide personal use?
No. Research articles can explain mechanisms, trial design and emerging evidence, but they are not personal medical advice and should not be used as instructions for treatment.
Bottom line
Retatrutide is a notable research topic because it targets GLP-1, GIP and glucagon receptors, placing it within a fast-moving area of metabolic science. For UK readers, the key point is caution: interest in “pens” should be separated from evidence, regulation and individual clinical care. The most reliable understanding will come from completed trials, regulatory decisions and official medical information, not from informal claims about access or use.
Intended for in-vitro laboratory research only. Not for human or animal consumption.